
The MISP: the minimum standard for sexual and reproductive health in emergencies
- Page updated onSeptember 21, 2026

In humanitarian crises, not only do gender systemic inequalities and discrimination against girls and women increase, but their freedom, rights, and health regarding sexuality and reproduction are also directly threatened. For this reason, it is essential to include essential sexual and reproductive health actions and services in emergencies that allow for the reduction of risks of gender-based violence, unintended pregnancies, sexually transmitted infections, and maternal health problems.
Table of contents:
How did the MISP emerge from earlier reproductive health progress in the 1990s?
The 1994 Cairo Conference gave a major boost to reproductive rights
In 1994, the International Conference on Population and Development was held in Cairo. This event and the resulting programme of action marked a turning point, defining reproductive health and rights and placing them among the priorities of public health and human rights (United Nations, 1994).
Thanks to this and other subsequent advances, we now understand that achieving the right to health depends on progress towards reproductive health, gender equality and women's empowerment (UNFPA, 2019). This requires the rights and freedoms of all people to be upheld and respected, namely the right to:
- Have their personal autonomy, bodily integrity and privacy respected.
- Define their sexuality, sexual orientation, gender identity and how to express it.
- Choose their partners.
- Have safe and pleasurable sexual experiences.
- Decide whether or not, when and with whom they want to get married.
- Decide whether or not, when and how to have one or more children.
- Access the information, resources, services and support necessary to exercise all other rights, free from discrimination, coercion, exploitation and violence.
Those years also saw a shift from maternal health to reproductive health in humanitarian contexts
At the same time as the Cairo conference was taking place, reproductive health was also beginning to be seen as a priority in humanitarian settings and complex emergencies (Wulf, 1994). The use of sexual and gender-based violence as a weapon of war, for instance, was widely denounced in the humanitarian emergencies of this period. In Rwanda, between 100,000 and 250,000 women were raped during three months of genocide in 1994. Likewise, during the war in Bosnia (1992-1995), between 10,000 and 50,000 women were raped, in some cases repeatedly over years in civilian concentration camps. In those years, the world witnessed the fragility of the sexual and reproductive health and rights of millions of women affected by humanitarian crises (IAWG, 2004).
The report "Refugee Women and Reproductive Health Care: Reassessing Priorities", published in 1994 by what is now the Women's Refugee Commission, examined the state of reproductive health and rights among displaced and refugee women in Côte d'Ivoire, Rwanda, Kenya, Pakistan, Belize, Thailand, Cambodia and Hong Kong (Wulf, 1994). This critical analysis of reproductive health needs also drove the development of new international coalitions. These included the Inter-Agency Working Group on Reproductive Health in Crises in 1995, and the Reproductive Health Response in Conflict Consortium (Chynoweth, 2015).
What is the MISP? A minimum package of sexual and reproductive health services in emergencies
The MISP emerged as a minimum initial service package within an inter-agency field manual
The twentieth century saw one last major milestone for reproductive health in humanitarian settings: the development, between 1996 and 1999, of the Inter-Agency Field Manual on Reproductive Health in Humanitarian Settings. This document and its successive updates in 2010 and 2018 (the current one) have laid the foundations and built consensus around which sexual and reproductive health services matter most in humanitarian settings, particularly for girls and women, while protecting their lives with dignity (IAWG, 2018).
The Field Manual also defined a minimum set of sexual and reproductive health actions for humanitarian emergency response: the Minimum Initial Service Package for Sexual and Reproductive Health in Crisis Situations, or simply the MISP. This set of priority actions emerged between 1996 and 1999 and has been significantly updated twice, in 2004 and 2018 (IAWG, 2018). In 2010 it was also included as a standard in the Sphere Handbook. Today it is a powerful tool for advocacy, coordination and the programming of these actions (Chynoweth, 2015).
The MISP sets out 6 objectives for sexual and reproductive health
The MISP was established to prevent sexual and reproductive health needs from being overlooked in humanitarian crisis response. It therefore covers the essential services that should always be available within the first 48 hours of any emergency. They are needed to prevent illness and death and to protect the right to life with dignity, particularly for women and girls (WRC & IAWG, 2021).
The MISP's minimum health services were defined to achieve 6 objectives:
- Ensure the health sector or cluster identifies an organisation to lead the implementation of the MISP itself. This objective concerns the coordination and information management structure needed to achieve all the others.
- Prevent sexual and gender-based violence and respond to the needs of survivors. This objective covers not only health care services and referral to other support services, but also guarantees of safety and confidentiality in health facilities and the necessary collaboration with other humanitarian sectors, such as protection, to reach people exposed to sexual and gender-based violence.
- Prevent the transmission of HIV/AIDS and other sexually transmitted infections and reduce the illness and death they cause. This requires a series of precautions in health services, along with the availability of condoms, antiretrovirals to continue treatments and any programmes already under way to prevent mother-to-child transmission, post-exposure prophylaxis for survivors of gender-based violence, and the diagnosis and treatment of these conditions and other opportunistic infections.
- Prevent excess maternal and newborn illness and death. The key to achieving this objective is the availability of accessible emergency obstetric and newborn care services at several levels of care, with the communication and transport means needed to sustain the referral system.
- Prevent unintended pregnancies. The fifth objective, closely tied to the reproductive rights of women and girls, requires the availability of information and a wide range of contraceptive methods.
- Plan comprehensive sexual and reproductive health services integrated into primary health care as soon as possible. The final MISP objective concerns expanding services beyond the minimum essential components, from a standpoint of resilience and health system strengthening.
Alongside these six objectives, the MISP sets out other additional priorities for sexual and reproductive health, notably ensuring access to safe abortion care, to the full extent of the law (WRC & IAWG, 2021). It is important to be clear about the distinction between this priority and post-abortion care, covered under the MISP's fourth objective to treat miscarriages or abortions that have already been induced, and their complications.
In protracted humanitarian crises and stable settings, minimum sexual and reproductive health services are not enough
Some experts criticise the MISP for covering so many objectives that it is no longer minimum, nor realistic for certain contexts (Tran & Schulte-Hillen, 2018). They argue that amid the insecurity and chaos of a humanitarian emergency, prioritising is unavoidable. They also point out that this should be done on the basis of scientific evidence, people's rights, and what is acceptable and feasible to deliver in the first days of a crisis response. They further criticise the latest MISP update for failing to take into account the voices of some key actors.
At the same time, there are other contexts where, although needs call for MISP objective 6 to be prioritised and the available services expanded, this does not actually happen (IAWG, 2004). This can be particularly marked in protracted humanitarian crises. There, once the most immediate phase of the response has passed and its strict prioritisation with it, significant needs go unmet unless the limitations inherent to a minimum service package are overcome (GHC, 2025). These include sex education, better quality follow-up of pregnancy and antenatal visits, a more comprehensive approach to menstrual health and menstrual hygiene management, and care for cervical cancer or fertility problems, for example (Starrs et al., 2018).
There is consensus that meeting these needs should not divert resources from higher priorities in the early phases of a humanitarian emergency. This, however, need not conflict with the importance of expanding the necessary services when it becomes feasible to do so, in pursuit of the goal of universal health coverage (UNFPA, 2019). And that requires a coherent transition from one approach to the other (WHO et al., 2011), guided by a vision that properly integrates the nexus between development cooperation and humanitarian action (Qaddour et al., 2026). From this standpoint, moreover, all health systems should be resilient and therefore ready to guarantee the MISP within 48 hours when an emergency occurs (Family Planning 2020, 2020).
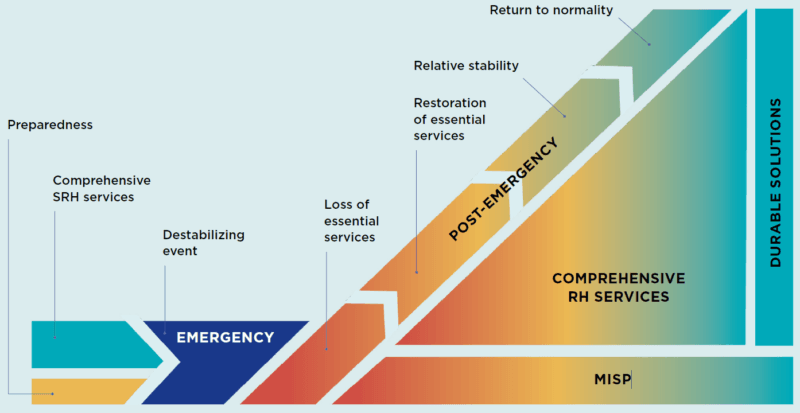
Many voices also insist that addressing sexual and reproductive health in humanitarian crises cannot, in any case, be reduced to a minimum package of health services. These services should be understood as one component of a comprehensive, multisectoral approach to promoting, protecting and respecting the human rights of women and girls in humanitarian settings, one that also tackles gender discrimination and inequality (OHCHR, 2022).
Why do the 2025 humanitarian funding cuts put the MISP at risk?
Before humanitarian funding was drastically reduced, much remained to be done in the area of reproductive rights
By around 2023, progress on maternal and reproductive health had already slowed considerably. Each year, 300,000 maternal deaths were still being recorded (Starrs et al., 2018). Of these, an estimated 200,000 occurred in humanitarian settings (WRC & IAWG, 2021).
This stalling was linked to the impact of the COVID-19 pandemic, the global economic crisis stemming from the conflict in Ukraine and the growing debt burden in Africa, as well as to the chronic lack of political will and to gender inequality (Bhutta & Rulisa, 2025).
At that point, funding for sexual and reproductive health was already insufficient and poorly targeted. Concentrated in certain programmes, such as those for the fight against HIV/AIDS, it left aspects such as family planning, gender-based violence and the empowerment of local women-led organisations in the background. Serious gaps also persisted in the availability of emergency obstetric and newborn care and in access to safe abortion, along with a huge information gap on the impact of crises on LGBTIQ+ people.
Multiple evaluations showed that funding was not the only problem. Sustaining the political commitments to take on the MISP and maintaining the structures needed for its coordination was a challenge in places such as Chad and Ethiopia, for example. In other contexts, such as Mozambique, the MISP was seen as the basis for routine reproductive health services, despite being a minimum standard designed for humanitarian emergencies in which prioritising only essential services is critical (GHC, 2025). All these fragilities became even clearer in 2024 and finally from 2025 onwards, when humanitarian funding was drastically cut
Financial, ideological and political pressure on sexual and reproductive health threatens the prospects of guaranteeing the MISP in humanitarian emergencies
In early 2025 there was a drastic shift in United States foreign and health policy. After an initial freeze on funds, 80% of USAID grants were terminated. This dismantled the aid provided by the donor that channelled 30% of all global health funding and 40% of family planning funding (Singh et al., 2025). It was done, moreover, in a deliberately abrupt manner, leaving no room for these needs to be covered by other means (Bhutta & Rulisa, 2025).
The first consequences were not long in coming. Reproductive health projects were halted immediately and important coordination mechanisms, needed to guarantee the MISP, disappeared (GHC, 2025). Among the consequences of this upheaval, it was estimated that more than 11 million women and girls would lose access to contraception, which could result in over 4.2 million unintended pregnancies and more than 8,000 additional maternal deaths in a single year (Sully et al., 2025).
This is not only a reduction in funding for reproductive health and rights, but also an enormous ideological and political pressure (Singh et al., 2025). This is reflected, for example, in the reinstatement and expansion of the gag rule barring international organisations that receive US funds from providing information on legal abortion services. The Geneva Consensus Declaration was also signed again, an anti-abortion coalition that repudiates internationally recognised reproductive rights while seeking support and further country signatories. At the same time, the donor has ended its contributions to agencies such as UNFPA, WHO, UNAIDS and UN Women, and introduced great uncertainty over the funding of other key international programmes and initiatives.
It will be some time before the global impact of these measures is known. Its possible repercussions include the loss of lives and greater suffering for millions of women and girls and their families (GHC, 2025), but also the erosion and collapse of many of the gains made over the years, and with great effort, in human and reproductive rights.
🧠 Let's pause and reflect
In a context of drastically reduced humanitarian funding and increasing political pressure on reproductive rights, how should humanitarian organizations defend and sustain the gains made in sexual and reproductive health?
- 1Think and write your answer.
- 2Click on «Copy and open».
- 3Paste to receive feedback.
📚 This is the NotebookLM for this topic. It uses only carefully selected references. | What is NotebookLM?
References
- Bhutta, Z. A., & Rulisa, S. (2025). Implications of the USAID U-turn on women’s health globally [Editorial]. Obstetric Medicine, 18(2), 67–68. https://doi.org/10.1177/1753495X251332669
- Chynoweth, S. K. (2015). Advancing reproductive health on the humanitarian agenda: The 2012-2014 global review. Conflict and Health, 9(Suppl. 1), Article I1. https://doi.org/10.1186/1752-1505-9-S1-I1
- Family Planning 2020. (2020). Ready to save lives: A preparedness toolkit for sexual and reproductive health care in emergencies. https://www.fp2030.org/app/uploads/2023/07/SRH_preparedness_toolkit.pdf
- Global Health Cluster. (2025). The Minimum Initial Service Package for Sexual and Reproductive Health: Process evaluation. Cross-contexts synthesis: Chad, Ethiopia, Gaza, and Mozambique. World Health Organization. https://healthcluster.who.int/publications/m/item/the-minimum-initial-service-package-for-sexual-and-reproductive-health
- Inter-Agency Working Group on Reproductive Health in Crises. (2004). Report of an inter-agency global evaluation of reproductive health services for refugees and internally displaced persons. https://iawg.net/resources/2004-inter-agency-global-evaluation-of-reproductive-health-services-for-refugees-and-internally-displaced-persons
- Inter-Agency Working Group on Reproductive Health in Crises. (2018). Inter-agency field manual on reproductive health in humanitarian settings. https://www.iawgfieldmanual.com/
- Qaddour, A., Tappis, H., Lazieh, S., Ward, A., & Spiegel, P. (2026). The humanitarian-development nexus and sexual and reproductive health interventions in fragile settings: A scoping review. PLOS Global Public Health, 6(2), Article e0005767. https://doi.org/10.1371/journal.pgph.0005767
- Singh, S., Sedgh, G., Sully, E. A., Owolabi, O., & Wittenberg, J. (2025). Protecting global sexual and reproductive health and rights in the face of retrograde US policies and positions [Comment]. The Lancet, 405(10490), 1650–1653. https://doi.org/10.1016/S0140-6736(25)00618-X
- Starrs, A. M., Ezeh, A. C., Barker, G., Basu, A., Bertrand, J. T., Blum, R., Coll-Seck, A. M., Grover, A., Laski, L., Roa, M., Sathar, Z. A., Say, L., Serour, G. I., Singh, S., Stenberg, K., Temmerman, M., Biddlecom, A., Popinchalk, A., Summers, C., & Ashford, L. S. (2018). Accelerate progress—sexual and reproductive health and rights for all: Report of the Guttmacher–Lancet Commission. The Lancet, 391(10140), 2642–2692. https://doi.org/10.1016/S0140-6736(18)30293-9
- Sully, E. A., Owolabi, O., & Rosenberg, J. D. (2025, January 29). Family planning impact of the Trump foreign assistance freeze. Guttmacher Institute. https://www.guttmacher.org/2025/01/family-planning-impact-trump-foreign-assistance-freeze
- Tran, N. T., & Schulte-Hillen, C. (2018). Wishful thinking versus operational commitment: Is the international guidance on priority sexual and reproductive health interventions in humanitarian settings becoming unrealistic? Conflict and Health, 12, Article 32. https://doi.org/10.1186/s13031-018-0157-x
- United Nations. (1994). Report of the International Conference on Population and Development, Cairo, 5-13 September 1994 (A/CONF.171/13/Rev.1). http://undocs.org/A/CONF.171/13/Rev.1
- United Nations High Commissioner for Human Rights. (2022). Comprehensive approach to promoting, protecting and respecting women’s and girls’ full enjoyment of human rights in humanitarian situations (A/HRC/49/37). https://www.ohchr.org/en/documents/thematic-reports/ahrc4937-comprehensive-approach-promoting-protecting-and-respecting
- United Nations Population Fund. (2019). Sexual and reproductive health and rights: An essential element of universal health coverage. https://www.unfpa.org/featured-publication/sexual-and-reproductive-health-and-rights-essential-element-universal-health
- Women’s Refugee Commission, & Inter-Agency Working Group on Reproductive Health in Crises. (2021). Minimum Initial Service Package (MISP) for Sexual and Reproductive Health (SRH) in crisis situations: A distance learning module. https://iawg.net/resources/minimum-initial-service-package-distance-learning-module/
- World Health Organization, United Nations Population Fund, & Andalusian School of Public Health. (2011). Sexual and reproductive health during protracted crises and recovery (WHO/HAC/BRO/2011.2). World Health Organization. https://www.who.int/publications/i/item/sexual-and-reproductive-health-during-protracted-crises-and-recovery
- Wulf, D. (1994). Refugee women and reproductive health care: Reassessing priorities. Women’s Commission for Refugee Women and Children. https://www.womensrefugeecommission.org/wp-content/uploads/2020/04/Reassessing-Priorities-1994-web.pdf
NotebookLM
You can review my bibliographic references on reproductive health and rights in emergencies with this NotebookLM, an artificial intelligence-based research assistant. Do you want to know more?
How to cite this page
Abarca, B. (September 21, 2026). The MISP: sexual and reproductive health standards in humanitarian response. Salud Everywhere. https://saludeverywhere.com/en/health-in-humanitarian-crises/reproductive-health-and-rights-in-emergencies/