
Social determinants of health and humanitarian crises
- Page updated onOctober 15, 2026

A large share of health problems stem from the conditions in which people are born, grow, live, work and age. Inequality in those conditions is the result of a toxic combination of poor social policies and programmes, unfair economic arrangements, and bad politics (CSDH, 2008).
For this reason, addressing the social determinants of health also requires putting an end to the unequal distribution of power and economic resources and placing health at the heart of humanitarian action.
Table of contents:
What affects the health of people and their communities?
Access to health care is not everything
Before looking at how humanitarian crises affect health, we need to understand what determines people's health in the first place. And on this, scientific evidence has steadily transformed the early theories.
For a long time it was thought that removing the financial barriers to health care across all social classes would narrow the health gradient between them. In other words, it was believed that making health care accessible to everyone would make the differences in health status and life expectancy between rich and poor disappear.
This belief was called into question, however, once illness was linked to living conditions, particularly towards the end of the twentieth century. This came about, among other things, through a series of studies published in the United Kingdom, such as the Black Report of 1980, the Whitehall studies from 1967 onwards, and the Acheson Report of 1998. These studies showed that health care is not everything and that people's health is in fact largely shaped by their social and economic circumstances (Marmot, 2022).
How and where you live matters
Some lines of research focused on estimating the weight of factors such as genetics, social circumstances, environmental conditions, behaviours and medical care in premature mortality (McGinnis et al., 2002). Other approaches, however, concentrated on a different question: why these factors clustered more in some people than in others. Answering that question gave considerable impetus to the concept of the social determinants of health.
These determinants included factors as significant as socioeconomic status, the psychosocial circumstances that cause stress, opportunities for education and development in the early years of life, poverty and social exclusion, working conditions, unemployment, support networks and social cohesion, addiction, diet and transport, which in turn largely shape exercise, social interaction and exposure to pollution (Wilkinson & Marmot, 2003).
At the same time, the crucial relationship between the social determinants of health and health inequity became clear. This is what explains that social injustice is killing people on a grand scale, and that economic growth without social policies can never be enough (CSDH, 2008).
Finally, once the scientific evidence on the social determinants of health and health equity was available, it moved beyond academic circles to influence public policy and the global health agenda (WHO, 2011).
Conceptual frameworks of the social determinants of health
Today there are several frameworks that help us understand what the social determinants of health and of health inequity are and how they relate to one another. At the same time, they make it possible to identify potential actions to address them all and to develop further frameworks for monitoring them (WHO, 2024).
The Dahlgren and Whitehead rainbow, 1991
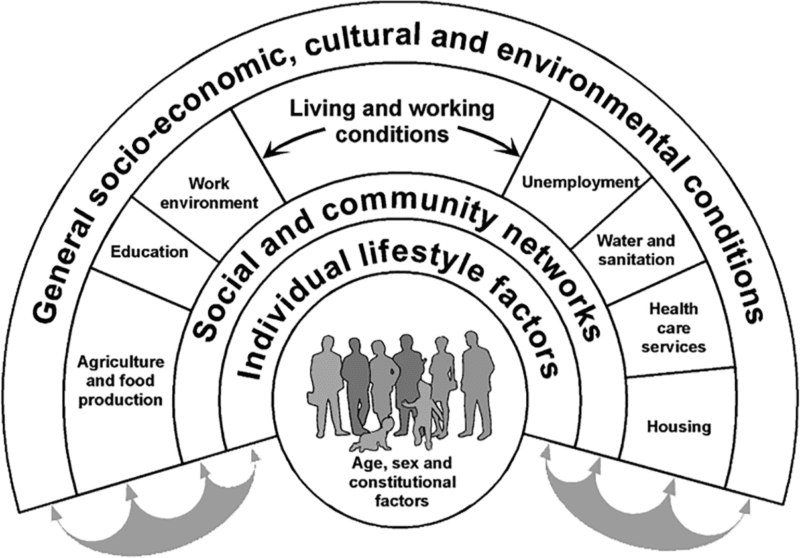
One of the best-known models is the one proposed in 1991 by Göran Dahlgren and Margaret Whitehead. It was originally designed to bring these complex ideas into the realm of public policy on health inequalities. It represents the basic influences on health as concentric arcs of a rainbow, ranging from general conditions through social and community networks to the factors tied to individual lifestyles (Dahlgren & Whitehead, 1991/2007).
Health at the end of a causal process that begins in social structures
Although less well known than the previous one, in 2004 Hilary Graham published a simple model that helps make sense of the causal pathway linking social factors to health and illness.
This model takes as its starting point social structure and the social position an individual occupies within its hierarchy, according to their finances, ethnicity and gender, among other things. This shapes the inflow of social and material resources such as education, employment, income, property or political influence. Access and exposure to these resources are largely determined by that social position, which is a source of inequity (Graham, 2004). These in turn shape physiological and behavioural factors, such as obesity or taking exercise, which govern vulnerability to illness.
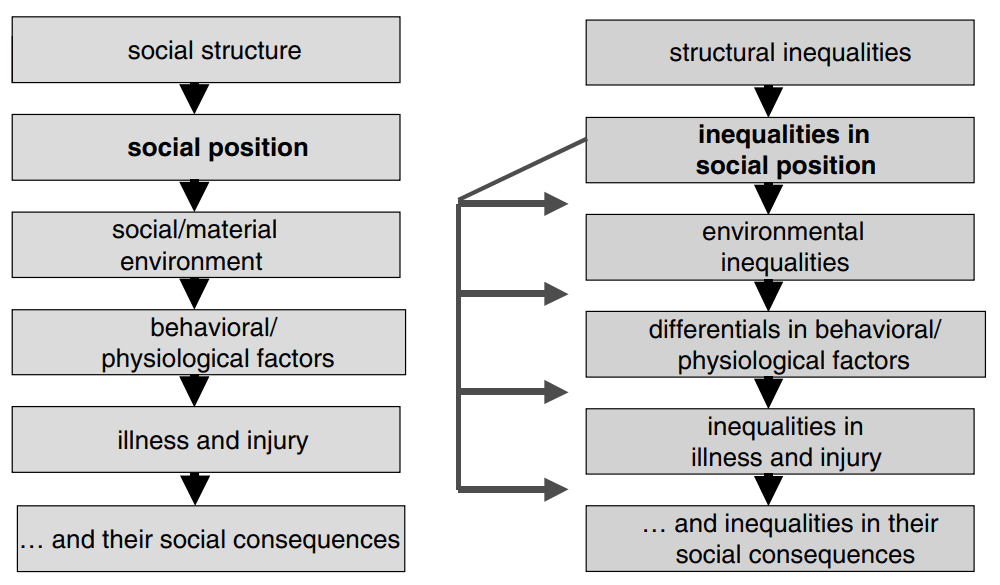
This model gives a clear picture of how inequalities at each level drive inequalities at the levels below. It also clarifies a conceptual distinction that is essential if research is to translate into policy: the social determinants of health are one thing, and the social determinants of health inequalities are another. A policy agenda that pursues health equity must address both.
The Solar and Irwin framework: structural and intermediary determinants of health
Arguably the most influential conceptual framework on this subject is the one developed by Orielle Solar and Alec Irwin for the Commission on Social Determinants of Health (Solar & Irwin, 2010).
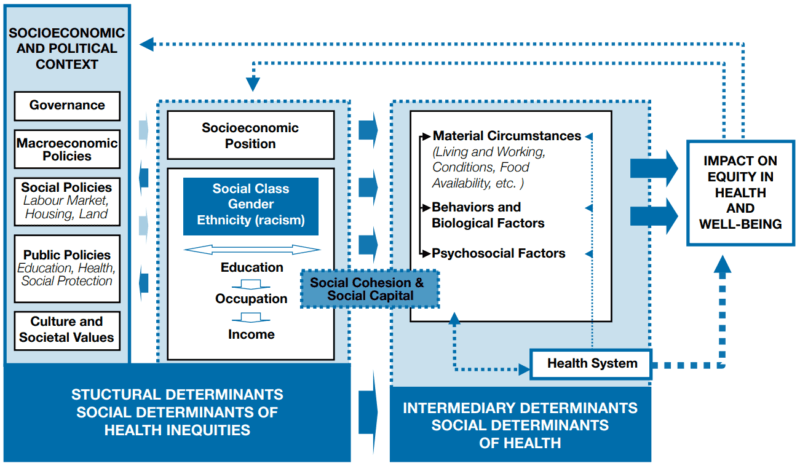
This framework adopts the distinction set out by Graham and clearly separates two groups of determinants:
- The social determinants of health, or intermediary determinants. These answer the question of what makes people ill or healthy, and they map onto the list of ten factors put forward by Wilkinson and Marmot in 2003. The authors group them, more or less, into three broad blocks: material circumstances, behavioural and biological factors, and psychosocial factors. They also connect the health system and access to health services at this level.
- The social determinants of health inequity, or structural determinants. These explain why the intermediary determinants are distributed unevenly across different social groups, or why some people fall ill more than others. This is where the prevailing socioeconomic and political context comes into play, along with social position. It is these factors that widen the gradient and the gap between rich and poor, for example, and that is why they must be acted on, and not only the social determinants of health.
- Between the two levels, and cutting across both, lie social cohesion and social capital.
The commercial determinants of health
Over time, the social determinants of health have come to be heavily influenced by market logic, industry and large multinational corporations. Although these can also contribute to health benefits, they likewise cause harm and externalise the costs of doing so. These factors, which bear on both the social determinants of health and the social determinants of health equity, have been termed the commercial determinants of health (Gilmore et al., 2023).
The commercial determinants of health are shaped by industries such as tobacco, alcohol and ultra-processed foods. Their impact on breastfeeding practices and on the prevalence of non-communicable diseases such as diabetes and cancer is well documented (PHM, 2025). Yet they have a systemic effect that goes far beyond isolated consequences, one that harms the planet, deepens inequity and erodes public health and global health.
The actors behind the commercial determinants of health wield enormous influence over public policy in pursuit of their own economic interests. These policies, in turn, result in the circulation and consumption of products that are harmful to health, and in the externalisation of the costs of that harm. It is people, their communities and states that ultimately bear the consequences and the cost of the rise in chronic diseases, for example, while companies increase their profits and power, creating a vicious circle (Gilmore et al., 2023).
New social determinants of health equity: conflict, climate change, and digitalisation
In 2025, the World Health Organization, in a review of the social determinants of health equity, or structural determinants, following the Solar and Irwin conceptual framework, added new elements (WHO, 2025).
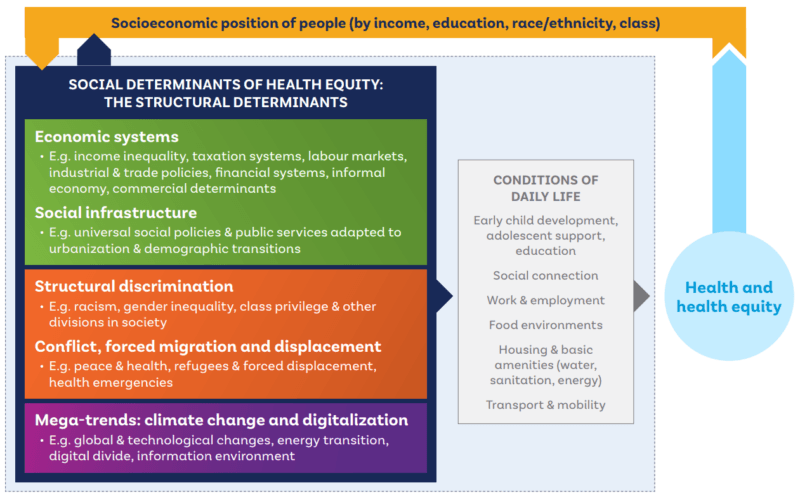
These include major new factors and trends with a profound impact on human and planetary health: conflict, climate change (WHO, 2025) and digitalisation (Shaw et al., 2026). They align, too, with some of the major global threats to health identified by other authors, with the potential to become extinction-level risks in the case of nuclear conflict or the malicious use of artificial intelligence (Murray et al., 2026).
Inequality continues to widen the equity gap and worsen the social determinants of health
More than fifteen years have passed since what looked like the turning point for tackling the social determinants of health globally. Yet, despite sustained academic and public health interest, the expected shift in policy and action has not materialised.
Although many countries have made economic and social progress over this period, inequality has grown. In many countries, wealth is increasingly concentrated in extreme wealth and poverty in extreme poverty. There have also been pandemics and major financial and climate crises, alongside a resurgence of political movements that advocate cutting taxes and curbing wealth redistribution and social protection (WHO, 2025).
Major social determinants of health remain inadequately addressed
Health is still understood, in many cases, through the narrow lens of health care, and the ambitious primary health care approach has been overshadowed by the more care-focused targets of universal health coverage, whose progress has stalled.
The climate crisis and environmental degradation are also worsening. It now looks impossible for the sustainable development goals on food security to be met, and progress on reducing gender inequality has slowed so much that, at the current rate, it is estimated that more than a hundred years will still be needed to achieve it.
In humanitarian settings, all of this becomes more acute, especially when the problems generated by conflict and forced displacement grow faster than humanitarian funding and the protection of those affected.
The social determinants of health in emergencies: how do complex humanitarian crises affect health?
In complex humanitarian crises, multiple causal and triggering factors overlap, closely bound up with the social determinants of health and of health equity. Those factors are conflict, political instability, the collapse of public authorities and services, insecurity for the population and for those trying to assist them, forced displacement, hunger, epidemics and greater vulnerability to natural disasters.
The relationship between all of them and the structural and intermediary determinants of health is multidirectional and complex (WHO EMRO, 2008). On the one hand, in many cases the deterioration of the structural determinants of health itself helps to cause and precipitate humanitarian crises. On the other, when this happens, those pre-existing determinants, bound up with health inequity, deteriorate still further.
In humanitarian crises, the structural determinants of health are acutely affected
Armed conflict, forced displacement and migration, political instability and the collapse of public authorities and governance that occur in humanitarian crises are, in themselves, structural determinants of health.
In these circumstances, moreover, human rights are often lost, as people are exposed to violent attacks against themselves and those assisting them, and to an acute lack of security, as essential infrastructure is destroyed, social protection policies are interrupted, people become internally displaced or refugees, and social networks and the social fabric disintegrate (WHO EMRO, 2008).
It is also important to understand that humanitarian emergencies and all these determinants do not affect everyone equally. Crises amplify pre-existing inequities, whether of gender, age, disability, ethnicity or legal and migration status. This inequity is reflected, for instance, in the heightened risks of violence against women, or in the suffering endured by people living in poverty with serious conditions and no access to palliative care.
The inequality in media attention to humanitarian crises and the geopolitical interests of donors also work as a structural determinant that at times generates scandalous inequity. Between 2003 and 2005, for instance, two major humanitarian crises occurred: the conflict in Darfur (Sudan) and the Indian Ocean tsunami. Darfur was neglected by donors and public attention, with a slow and inadequate response that over two years barely reached $1.57 billion, or 60% of what had been requested for the joint humanitarian response plans. The tsunami, by contrast, received enormous media coverage and record levels of humanitarian funding, exceeding $13.5 billion in total funding, including private donations.
The worsening political and socioeconomic context in emergencies also erodes the intermediary determinants of health
The structural determinants of health that both cause humanitarian crises and deteriorate within them in turn affect the intermediary determinants of health. Families and communities lose their livelihoods and their access to land and employment, are exposed to extreme poverty and food insecurity, are left homeless or in precarious shelter, and are deprived of access to essential services such as water, sanitation, health care or education.
All of this has not only a physical and material impact, but an emotional and psychological one too. The violation of rights, the lack of protection, the deprivation of goods and services essential to survival and the dependence on humanitarian action to survive give rise in turn to feelings of fear, hopelessness, powerlessness and abandonment, and even to a loss of meaning in life (WHO EMRO, 2008).
Humanitarian crises have both a direct and an indirect impact on people’s health
The acute deterioration of the social determinants of health and of health equity that occurs in humanitarian crises and conflicts has an impact on people's health (Garry & Checchi, 2020).
These effects go far beyond the direct impact of violent attacks and the wounds, injuries and deaths they cause. In fact, the indirect impact, although it varies enormously between contexts, is usually considerably greater (Spiegel et al., 2026). Shaped by prior nutritional and health status, by the resilience of the health system and by access to services, it includes effects related to infectious diseases, epidemics, non-communicable diseases and the breakdown of continuity of care for chronic patients, as well as problems of maternal, reproductive and sexual health, mental health and malnutrition in its many forms.
Addressing the determinants of health in humanitarian response is necessarily multisectoral
Access to quality health care is certainly a social determinant of health, but it is not the only one. It may well not be the most important one either.
Humanitarian action cannot therefore look to the health sector alone to tackle health problems and illness. On its own, that sector can only help prevent certain conditions and provide health care to those who need it. But this is not enough.
Addressing health in humanitarian settings requires cooperation between organisations and responses across every sector. What is more, it is not enough for health to be treated as a secondary or incidental outcome: it must be placed at the heart of the objectives of humanitarian action (Spiegel et al., 2026).
References
- Commission on Social Determinants of Health. (2008). Closing the gap in a generation: Health equity through action on the social determinants of health (WHO/IER/CSDH/08.1). World Health Organization. https://www.who.int/publications/i/item/WHO-IER-CSDH-08.1
- Dahlgren, G., & Whitehead, M. (2007). Policies and strategies to promote social equity in health: Background document to WHO – Strategy paper for Europe (Arbetsrapport 2007:14). Institute for Futures Studies. https://iffs.se/policies-and-strategies (Original work published 1991)
- Gilmore, A. B., Fabbri, A., Baum, F., Bertscher, A., Bondy, K., Chang, H.-J., Demaio, S., Erzse, A., Freudenberg, N., Friel, S., Hofman, K. J., Johns, P., Abdool Karim, S., Lacy-Nichols, J., de Carvalho, C. M. P., Marten, R., McKee, M., Petticrew, M., Robertson, L., . . . Thow, A. M. (2023). Defining and conceptualising the commercial determinants of health. The Lancet, 401(10383), 1194–1213. https://doi.org/10.1016/S0140-6736(23)00013-2
- Garry, S., & Checchi, F. (2020). Armed conflict and public health: Into the 21st century. Journal of Public Health, 42(3), e287–e298. https://doi.org/10.1093/pubmed/fdz095
- Graham, H. (2004). Social determinants and their unequal distribution: Clarifying policy understandings. The Milbank Quarterly, 82(1), 101–124. https://doi.org/10.1111/j.0887-378X.2004.00303.x
- Marmot, M. (2022). Public health and health inequalities: A half century of personal involvement. Journal of Public Health, 44(Suppl. 1), i23–i27. https://doi.org/10.1093/pubmed/fdac095
- McGinnis, J. M., Williams-Russo, P., & Knickman, J. R. (2002). The case for more active policy attention to health promotion. Health Affairs, 21(2), 78–93. https://doi.org/10.1377/hlthaff.21.2.78
- Murray, C. J. L., Kanem, N., Abed, S., Abubakar, I., Adetifa, I. M., Aguilera, X. P., Asma, S., Capua, I., Chungong, M., Davies, S., Frenk, J., Galvão, L. A. C., Halton, S. J., Houser, T., Kyobutungi, C., Lima, N. T., Louzir, H., Meda, N., Monti, M., . . . Vollset, S. E. (2026). The Lancet Commission on 21st century global threats to health. The Lancet. Advance online publication. https://doi.org/10.1016/S0140-6736(26)01714-9
- People’s Health Movement. (2025). Commercial/corporate determination of health. In R. Labonté & C. Bodini (Eds.), Global Health Watch 7: Mobilizing for health justice. Daraja Press. https://phmovement.org/mobilizing-health-justice-global-health-watch-7
- Shaw, J., Gross, N., Saldaña-Tejeda, A., Atuire, C., Prainsack, B., Holly, L., & Kickbusch, I. (2026). The digital determinants of health: A new era for global public health. The Lancet. Advance online publication. https://doi.org/10.1016/S0140-6736(26)01292-4
- Solar, O., & Irwin, A. (2010). A conceptual framework for action on the social determinants of health (Social Determinants of Health Discussion Paper 2). World Health Organization. https://www.who.int/publications/i/item/9789241500852
- Spiegel, P., Martinez, E., Abrahim, O., Undie, C.-C., Altare, C., Schmid, B., Abbara, A., Bahattab, A., Bojorquez, I., Cantor, D., Jouhaud, R., Alier, K. K., Maxwell, D., Moya, A., Ontas, E., Rashid, S. F., Rao, M., Slim, H., Abdelhay, A., . . . Blanchet, K. (2026). Johns Hopkins Center for Humanitarian Health–Lancet Commission on health, conflict, and forced displacement: Health in a world of crises and impunity. The Lancet, 407, 2065–2140. https://doi.org/10.1016/S0140-6736(26)00564-7
- Wilkinson, R., & Marmot, M. (Eds.). (2003). Social determinants of health: The solid facts (2nd ed.). World Health Organization, Regional Office for Europe. https://iris.who.int/handle/10665/326568
- World Health Organization. (2011). Rio Political Declaration on Social Determinants of Health. https://www.who.int/publications/m/item/rio-political-declaration-on-social-determinants-of-health
- World Health Organization. (2024). Operational framework for monitoring social determinants of health equity. https://www.who.int/publications/i/item/9789240088320
- World Health Organization. (2025). World report on social determinants of health equity. https://www.who.int/publications/i/item/9789240107588
- World Health Organization, Regional Office for the Eastern Mediterranean. (2008). Social determinants of health in countries in conflict: A perspective from the Eastern Mediterranean Region (WHO Regional Publications, Eastern Mediterranean Series 32). https://iris.who.int/handle/10665/119883
NotebookLM
You can review my bibliographic references on the social determinants of health with this NotebookLM, an artificial intelligence-based research assistant. Do you want to know more?
How to cite this page
Abarca, B. (October 15, 2026). Social determinants of health and humanitarian crises. Salud Everywhere. https://saludeverywhere.com/en/health-in-humanitarian-crises/social-determinants-of-health/